
Anorectal Assessment and Treatment
Piles Treatment in Agra: Grades, Laser Options and Surgery
Piles, also called haemorrhoids or बवासीर (bawaseer), cause bleeding, prolapse, itching or a painful lump. Dr. Himanshu Yadav assesses these symptoms at Dr. Himanshu’s Clinic on Delhi Gate Road, Agra, and plans treatment around what the examination actually shows — bowel-habit correction, medicines, an office procedure, laser treatment or surgery. Rectal bleeding is not always piles, so the diagnosis comes before the treatment choice.
When Rectal Bleeding or Anal Pain Needs Prompt Assessment
Seek prompt medical assessment if bleeding is heavy or does not stop, stools are black or tar-like, you feel dizzy or faint, or pain and swelling are worsening quickly with fever or discharge. Severe abdominal pain, vomiting, unexplained weight loss or a marked change in bowel habit also needs evaluation. These symptoms have causes other than piles, including some that need urgent treatment.
Do not wait for a routine clinic reply, and do not delay while collecting reports. Go to the nearest emergency department if symptoms are severe.
Patient Education Video
After Piles Surgery: Video Guidance
This short Hindi video gives general postoperative guidance on bowel habits, diet, activity and situations in which a patient should contact a doctor after piles surgery. It provides general information and does not diagnose an individual symptom. Heavy bleeding, faintness, black stool, fever or rapidly worsening pain needs prompt, appropriate assessment.
Understanding Piles
What Are Piles?
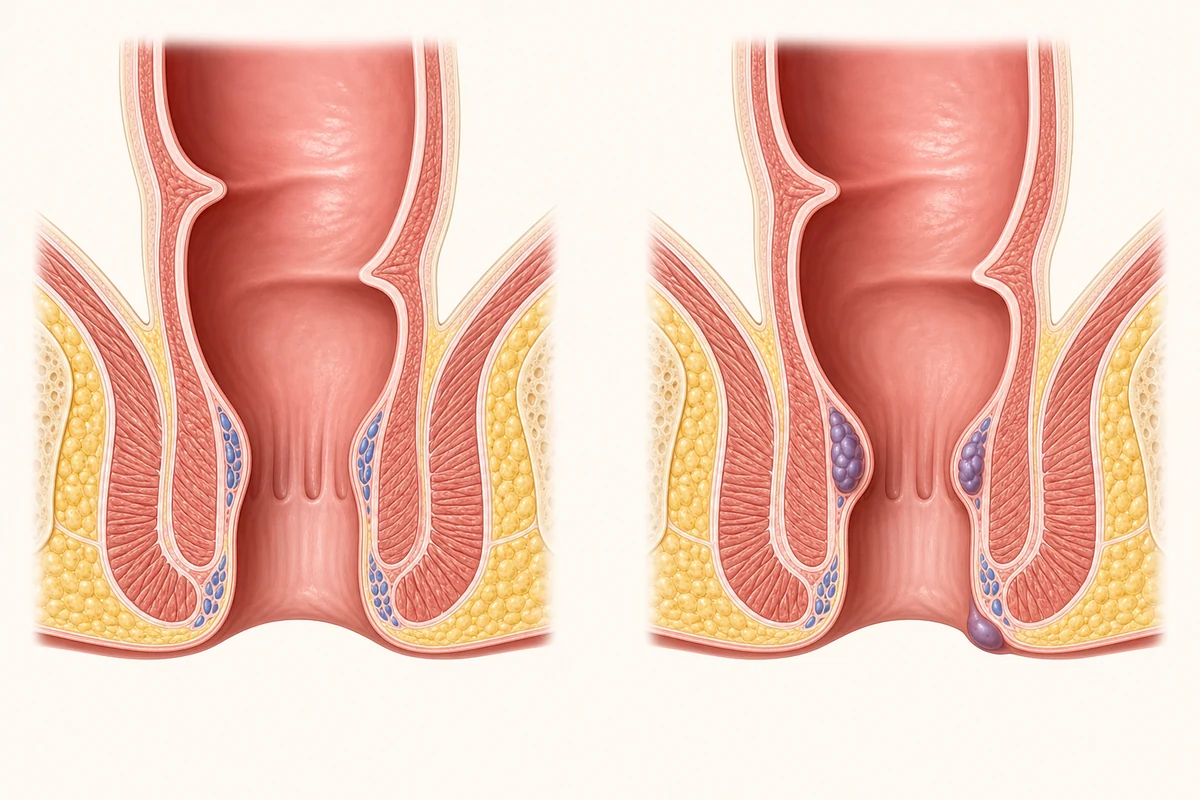
Piles are enlarged or symptomatic vascular cushions in the anal canal or around the anus. These cushions are a normal part of anal anatomy and help with closure and continence. They are called piles, haemorrhoids or bawaseer only when enlargement, displacement, inflammation or clotting starts producing symptoms — bleeding, prolapse, itching, mucus leakage, discomfort or a tender lump.
Internal and external haemorrhoids arise in different places and behave differently, which is why the treatment is not the same for everyone. The symptom pattern alone cannot confirm the diagnosis, because anal fissure, anal fistula, perianal abscess, rectal prolapse, inflammatory bowel disease, polyps and colorectal cancer can all produce overlapping complaints.
Types and Grades
Internal, External, Thrombosed and Mixed Piles
Internal haemorrhoids
These arise inside the anal canal, above the dentate line. They typically cause bright-red bleeding, mucus leakage or prolapse rather than severe pain, and they are graded by how far they protrude.
External haemorrhoids
These develop under the skin around the anus. They may cause swelling, irritation, difficulty with hygiene or discomfort. The Grade I–IV system does not apply to external haemorrhoids, which is a common source of confusion when patients compare treatment claims online.
Thrombosed external haemorrhoids
A clot can form inside an external haemorrhoid and cause a sudden, hard, very tender lump. This is one of the few piles presentations where timing genuinely matters: early assessment allows a wider range of options, whereas a lump that has already been present for several days is often managed with pain relief and bowel care while it settles on its own. If a new painful lump appears, arrange assessment early rather than waiting to see whether it improves.
Mixed haemorrhoids
Many patients have both internal prolapse and an external component. This matters more than most patients realise, because several widely advertised procedures treat the internal component well and do little for the external one. Treatment selection therefore depends on more than the internal grade alone.
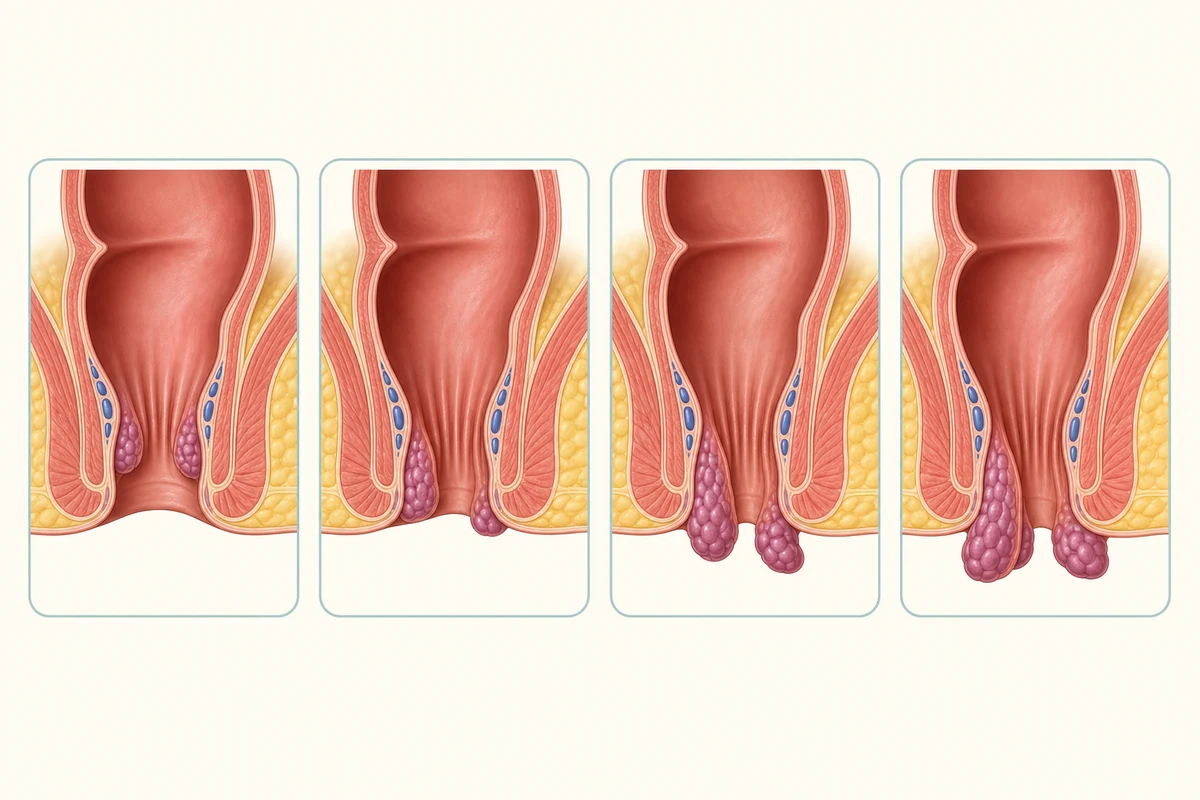
The Four Grades of Internal Piles
| Grade | What it means | Possible symptom pattern | Treatment implication |
|---|---|---|---|
| Grade I | Remains inside the anal canal | Bleeding or irritation without visible prolapse | Bowel-care measures are usually considered first; an office procedure may be discussed if symptoms persist. |
| Grade II | Prolapses during straining and returns by itself | Bleeding, mucus, itching or temporary prolapse | Conservative care, and selected office-based or minimally invasive options. |
| Grade III | Prolapses and needs to be pushed back manually | More persistent prolapse, bleeding, soiling or discomfort | Office treatment may suit selected cases; a laser or surgical option may be considered after assessment. |
| Grade IV | Remains prolapsed and is not easily reduced | Persistent prolapse, irritation, bleeding or discomfort | Surgical assessment is generally required; the operation depends on the internal and external components. |
Symptoms
Common Symptoms of Piles
- Bright-red bleeding
- Blood may appear on toilet tissue, on the surface of the stool, or in the toilet pan. Bleeding should not automatically be attributed to piles, particularly after the age of 40 or where there is a family history of bowel cancer.
- Prolapse or a lump
- Internal haemorrhoids may protrude during a bowel movement. External or thrombosed haemorrhoids may feel like a lump at the anal margin.
- Itching and irritation
- Mucus, moisture or skin irritation can cause itching. Dermatitis, fungal infection, worms and other conditions produce similar symptoms, so persistent itching deserves examination rather than repeated cream use.
- Discomfort or pain
- Internal haemorrhoids are often not painful. Marked pain suggests thrombosis, fissure, abscess or another diagnosis, and should be assessed rather than treated as ordinary piles.
- Mucus leakage or soiling
- Prolapse can interfere with anal closure and lead to mucus, dampness or difficulty keeping the area clean.
- A feeling of incomplete emptying
- Some people report pressure or the sense that the bowel has not fully emptied. Persistent change in bowel habit needs broader evaluation, not piles treatment alone.
Contributing Factors
What Can Contribute to Piles?
Piles rarely have a single cause. The factors below may increase pressure, straining or support-tissue change, but their presence does not prove why one individual developed symptoms.
- Constipation and repeated straining
- Prolonged sitting on the toilet, including phone use
- Frequent diarrhoea or repeated bowel movements
- Pregnancy and increased pelvic pressure
- Age-related changes in supporting tissue
- Heavy lifting or repeated increases in abdominal pressure
- Higher body weight in some patients
- Low fibre intake, or inadequate fluid intake where medically appropriate
These factors are discussed to improve bowel care and treatment planning, not to assign blame.
Consultation Triggers
When Should You See a Piles Specialist in Agra?
Arrange an assessment when rectal bleeding is new, persistent or recurrent; a lump or prolapse does not settle; pain is significant; symptoms return after treatment; or home measures have not helped. A consultation is equally appropriate when you simply do not know whether the problem is piles, a fissure, a fistula, an abscess or another bowel condition.
- Bleeding during or after a bowel movement
- Tissue that protrudes, or that has to be pushed back
- A new painful or tender external lump
- Recurrent itching, mucus or soiling
- Symptoms continuing despite fibre and bowel-habit measures
- Previous piles treatment followed by recurrent symptoms
- Anaemia, unexplained tiredness or repeated bleeding
- New or progressive change in bowel habit
- Abdominal symptoms, unexplained weight loss, or a family history of bowel cancer
- A wish for a second opinion before a procedure someone else has recommended
Before You Book
What Actually Happens at a Piles Consultation?
Embarrassment is the most common reason people delay this appointment, sometimes for years. It is worth knowing in advance exactly what a consultation involves, because the reality is usually far less daunting than people expect.
-
You talk first, fully clothed
The consultation begins as a conversation about bleeding, pain, prolapse, bowel habit, medicines, previous treatment and other health conditions. Many people find this is the longest part of the visit.
-
Examination is explained before it happens
Nothing is done without an explanation and your consent. You can ask what is being examined and why, and you can decline or defer any part of the examination. Examination takes place in a private room with the door closed, and takes only a few minutes.
-
A chaperone or attendant can be present
You may bring a family member. A female attendant can be requested for the examination.
-
Your information stays confidential
Clinical details are not shared without your consent, and are not used in any marketing material. No photographs of patients are published on this website. See our privacy policy.
-
Not every consultation ends in surgery
A large proportion of people who attend with bleeding or discomfort are managed with bowel-habit correction and medicines. Booking an assessment is not a commitment to a procedure.
Diagnosis
How Are Piles Diagnosed?
-
Symptom and health history
Bleeding, pain, prolapse, bowel habit, medicines, pregnancy, previous treatment, family history and other medical conditions are reviewed.
-
External inspection
The perianal skin is examined for an external haemorrhoid, thrombosis, fissure, fistula opening, abscess, irritation, prolapse or another visible cause.
-
Digital rectal examination
A focused examination may assess tenderness, masses, blood and anal muscle tone. The reason is explained and consent obtained first.
-
Proctoscopy or anoscopy where appropriate
A short instrument may be used to see the anal canal and internal haemorrhoids and to confirm the grade. Whether this is needed depends on the symptoms and examination.
-
Broader bowel evaluation when indicated
Blood tests, sigmoidoscopy or colonoscopy may be advised when no clear anorectal source is found, bleeding persists, or age, symptoms and risk factors require the colon and rectum to be examined. This step is how a treatable cancer is not missed behind an assumption of piles.
-
Shared treatment plan
Findings, grade, external component, alternatives, expected recovery and risks are reviewed before deciding between continued non-surgical care, an office procedure, laser treatment or surgery.
Conservative Care
Can Piles Be Treated Without Surgery?
Yes. Many mild internal haemorrhoid symptoms settle with bowel-habit change and short-term symptom relief, and no operation is needed. Non-surgical care is usually tried first unless the examination shows significant prolapse, thrombosis, another diagnosis, or some other reason to intervene earlier.
Fibre and fluids
Fibre makes stool softer and easier to pass. Fluid advice must be adjusted for anyone with kidney, heart or other conditions that limit intake, so general internet advice to "drink more water" is not universally safe.
Avoid straining
Do not delay the urge to pass stool, avoid repeated pushing, and keep time on the toilet short.
Treat constipation or diarrhoea properly
A stool softener, fibre supplement or another medicine may be advised after reviewing your bowel pattern and existing medicines.
Short-term symptom relief
Warm baths and selected creams, ointments or suppositories may ease mild discomfort or itching. These do not replace a diagnosis and should not be used indefinitely without advice — long-term use of some steroid-containing preparations can thin the perianal skin.
Reassess if symptoms persist
Recurrent bleeding, prolapse, a painful lump or symptoms that do not improve need review. Self-treatment should not be allowed to delay investigation of another cause.
Escalating Treatment
When May a Procedure or Surgery Be Considered?
A procedure may be considered when appropriate bowel care has not controlled symptoms, internal piles repeatedly prolapse, bleeding is recurrent, external or combined haemorrhoids remain troublesome, or a thrombosed external haemorrhoid needs early assessment. The decision rests on the diagnosis, grade, external component, previous treatment, anaesthetic risk, recovery priorities and your own informed preference.
- Recurrent or clinically significant bleeding
- Grade III or IV internal prolapse
- Large external, or combined internal-and-external, disease
- Persistent mucus leakage, irritation or hygiene difficulty
- Recurrent symptoms after an office procedure
- Severe pain from selected thrombosed external haemorrhoids
- Symptoms that substantially affect daily activity or work
- A second confirmed anorectal problem that can be treated at the same sitting
Surgery is not required merely because piles are present. The expected benefit should justify the discomfort, risks and recovery of the procedure being proposed.
Laser Treatment
Laser Piles Treatment in Agra: When It May Help
Laser treatment can be a useful option for selected patients with symptomatic internal haemorrhoids, but it is not a universal cure and is not automatically the best treatment. The decision depends on the source of bleeding, internal grade, degree of prolapse, external component, previous treatment, anaesthetic risk and your recovery priorities.
How laser haemorrhoid treatment works
A thin laser fibre is introduced into the haemorrhoidal tissue and controlled energy is applied so that the tissue shrinks and its blood supply is reduced. In laser haemorrhoidoplasty, the tissue is treated from within rather than removed as a wide open wound. This is one reason early pain may be lower than after conventional excisional surgery. It does not mean that the procedure is completely pain-free or that every external lump will disappear.
Laser techniques are not all the same
The term “laser piles treatment” can refer to different techniques. Laser haemorrhoidoplasty delivers energy into the haemorrhoidal tissue to reduce its volume; laser or Doppler-guided dearterialisation targets feeding vessels and may be combined with a lift of prolapsing tissue. These approaches are not interchangeable. Ask for the exact procedure, what tissue it is intended to treat and why it has been recommended.
When laser treatment may be discussed
- Selected Grade II and Grade III internal haemorrhoids after examination
- Patients whose main symptom is bleeding or internal prolapse rather than a large external lump
- Patients for whom less early postoperative discomfort and an earlier return to routine are important priorities
- Selected patients whose symptoms have persisted despite appropriate bowel care or an office procedure
When Laser May Not Be the Right Choice
Laser is not the right tool for every anatomical problem. It may not address the problem fully when the external or prolapsing component is the dominant complaint. In these situations, an office procedure, mucopexy, excisional surgery or another approach may provide a better anatomical solution.
- Large external skin tags or a big external component. Laser applied to internal tissue does not remove external skin.
- Fixed Grade IV prolapse or extensive tissue redundancy. Surgical assessment is usually important and an excisional operation may be more durable.
- An undiagnosed cause of bleeding. No procedure should be performed before the source of bleeding is established.
- A coexisting fissure, fistula or abscess. These have their own treatment pathways and may need to be addressed at the same time or first.
What the evidence supports, and what it does not
A 2023 systematic review and meta-analysis of nine studies involving 661 patients with Grade II or III haemorrhoids found less early pain, less analgesic use and an earlier return to work after laser haemorrhoidoplasty than after conventional haemorrhoidectomy. The same review reported a numerical trend towards higher haemorrhoidal symptom recurrence after laser at one year (28.6% versus 20.0% after conventional surgery), although the difference was not statistically significant. The apparent equivalence in bleeding, prolapse and complete resolution at 12 months rested on only two randomised controlled trials, so it should not be read as proof of long-term equivalence. A separate systematic review also found promising results but noted low study quality and substantial variation between techniques and follow-up periods. The practical conclusion is a possible early-recovery advantage in selected patients, not a guaranteed permanent cure.
Read the systematic review and meta-analysis (opens in a new tab) · Read the broader laser-treatment review (opens in a new tab)
No piles procedure can honestly be promised as painless, recurrence-free or a permanent cure in one sitting. A quoted success percentage is meaningful only when the procedure, patient selection, follow-up period and definition of success are stated.
Practical points patients ask about
- Anaesthesia: the plan may involve local anaesthesia with sedation, regional or spinal anaesthesia, or general anaesthesia, depending on the technique and facility.
- Stay: many cases are planned as day care, but observation may be advised according to anaesthesia, pain, bleeding, urine passage, other health conditions and home support.
- Bowel movements: the first few can still be uncomfortable. Stool-softening measures and avoidance of straining are important after treatment.
- Further treatment: some patients may need an additional procedure when residual prolapse, an external component or recurrent symptoms remain.
Questions to ask before choosing laser
- What is my confirmed diagnosis and internal grade?
- Do I have an external or mixed component that laser will not treat?
- Which exact laser technique is being proposed, and why?
- What are the non-surgical, office-based and conventional alternatives?
- What anaesthesia, observation, recovery and follow-up should I realistically expect?
- What is included in the written estimate, and what might require additional treatment?
Recognised Options
Piles Treatment and Surgery Options Compared
Treatment is selected after the diagnosis and grade are confirmed. The options below are recognised treatments for haemorrhoidal disease. Which of them are appropriate for you, and which are available at the treating facility, is confirmed at consultation.
Office-based treatment
Rubber band ligation, injection sclerotherapy or infrared coagulation may be considered for selected internal haemorrhoids, commonly Grade I–II and some Grade III disease, after conservative care. These do not treat an external component, and repeat sessions are sometimes needed. Band ligation is generally avoided in patients on blood thinners.
Laser haemorrhoidoplasty
Covered in detail in the laser section above.
Excisional haemorrhoidectomy
This operation removes symptomatic haemorrhoidal tissue and may be considered for large external haemorrhoids, combined internal-and-external disease, or Grade III–IV prolapse. It gives the most durable symptom control of the options listed here, at the cost of more postoperative discomfort and a longer recovery.
Doppler-guided haemorrhoidal artery ligation
Arterial branches supplying the haemorrhoids are identified and tied off, sometimes combined with a lift of prolapsing tissue. Postoperative pain is usually less than after excisional surgery, but recurrence has been higher in several comparisons. It does not address an external component.
Stapled haemorrhoidopexy
Stapling lifts prolapsing internal tissue rather than removing external haemorrhoids. It is not recommended as a routine first-line surgical treatment because of efficacy and risk considerations, including uncommon but serious complications. It should not be presented as a preferred option.
| Option | What it aims to do | When it may be discussed | Important limitation |
|---|---|---|---|
| Bowel care and medical treatment | Reduce straining, constipation and irritation | Mild Grade I–II symptoms, and alongside other treatments | Does not correct established prolapse or an external component. |
| Office-based procedure | Reduce blood flow to, or scar, selected internal tissue | Persistent Grade I–II and selected Grade III internal disease | May need repeat sessions; unsuitable for external or advanced disease. |
| Laser haemorrhoidoplasty | Shrink internal haemorrhoidal tissue with controlled laser energy | Selected Grade II–III internal or combined patterns, after assessment | Not universally superior; recurrence and suitability vary; does not remove external skin tags. |
| Excisional haemorrhoidectomy | Remove symptomatic internal and external tissue | Large external, combined or advanced prolapsing disease | More postoperative pain and a longer recovery than the alternatives. |
| Doppler-guided ligation | Reduce arterial inflow and lift prolapsing tissue | Selected internal prolapse | Recurrence may be higher than after excisional surgery. |
| Stapled haemorrhoidopexy | Reposition prolapsing internal tissue | Selected internal prolapse only | Does not address external disease; not recommended routinely first-line. |
Grade-Led Planning
How Is Treatment Matched to the Grade of Piles?
| Classification | Usual starting point | When an intervention enters the discussion |
|---|---|---|
| Grade I internal | Fibre, appropriate fluids, bowel-habit correction, short-term symptom relief | Persistent bleeding or symptoms may lead to an office procedure. |
| Grade II internal | Conservative care first | Office-based treatment, laser or another procedure where bleeding or prolapse persists. |
| Grade III internal | Assessment of prolapse, symptoms and external component | Selected office treatment, laser treatment or surgery may be discussed. |
| Grade IV internal | Surgical assessment | An operation is usually considered; the technique depends on anatomy, external disease and general health. |
| Thrombosed external | Early assessment, pain control and bowel care | Selected patients benefit from early excision; grade terminology does not apply. |
| Mixed internal and external | Assessment of both components | A treatment that addresses the full symptom pattern is usually required. |
This is a general pathway, not a prescription. Symptom severity, bleeding, previous treatment, examination findings and your own priorities can all change the plan.
Other Health Conditions
Piles With Diabetes, Pregnancy, Blood Thinners or Older Age
Coexisting conditions do not rule out treatment, but they change how it is planned, when it is done and what precautions are taken. Bring your full medicine list to the consultation, including anything bought without a prescription.
Diabetes
Wound healing and infection risk need attention, and glucose control is reviewed before any planned procedure. Perianal infection in a person with poorly controlled diabetes can progress quickly and should be assessed promptly rather than managed at home.
Blood thinners and antiplatelet medicines
Warfarin, newer oral anticoagulants, aspirin and clopidogrel all affect bleeding risk. Never stop these on your own. Whether, when and how they are adjusted is decided together with the doctor who prescribed them, and some procedures are preferred over others in this situation.
Pregnancy and after childbirth
Piles are common in pregnancy and often improve after delivery. Management during pregnancy is usually conservative, with attention to constipation, and medicine choices are restricted. Elective procedures are generally deferred, and any bleeding in pregnancy should be reported rather than assumed to be piles.
Older patients and heart, lung or kidney disease
Anaesthetic assessment carries more weight than the piles grade in these cases. A less invasive option with a lower anaesthetic requirement may be preferred even where a larger operation would give a more complete result.
Inflammatory bowel disease or immunosuppression
Anorectal symptoms in Crohn's disease in particular are managed differently, and routine haemorrhoid surgery may be inadvisable. Tell the clinician if you have any diagnosed bowel disease or take immune-suppressing medicines.
Differential Diagnosis
Piles, Anal Fissure, Anal Fistula or Rectal Prolapse?
These conditions overlap, and symptoms alone cannot always separate them. This table helps you recognise common patterns. It does not replace examination.
| Condition | Common symptom pattern | What may be seen or felt | Why the diagnosis matters |
|---|---|---|---|
| Piles (haemorrhoids) | Bright-red bleeding, prolapse, itching, mucus or a lump; marked pain suggests thrombosis or another problem | Internal tissue that prolapses, or an external lump | Treatment depends on internal grade, external component and symptoms. |
| Anal fissure | Sharp pain during and after stool, often with a small amount of bright-red blood | A small tear in the anal lining | Early fissures often settle with bowel care and medicines; chronic fissures follow a different pathway. |
| Anal fistula | Recurrent swelling, abscess episodes, pain or persistent pus discharge | An external opening or a tender area near the anus | The tract and its relationship to the sphincter determine treatment; antibiotics alone do not remove a fistula tract. |
| Rectal prolapse | Tissue protrusion, mucus, incomplete emptying or continence problems | A ring or segment of rectal wall protruding | It is not treated as piles and needs broader pelvic-floor and colorectal assessment. |
Anal Fissure Treatment Anal Fistula Treatment Rectal Prolapse Care Colorectal Surgery
Preparation
How to Prepare for Piles Treatment
- Bring a list of your current medicines and any allergies.
- Bring relevant blood tests, endoscopy reports and previous treatment or operation records.
- Tell the clinician about blood thinners, diabetes, heart or kidney disease, pregnancy and any previous anaesthetic problem.
- Follow only the fasting, bowel-preparation and medicine instructions issued for your specific procedure.
- Arrange transport and support at home if sedation or anaesthesia is planned.
- Ask what pain relief, stool softeners and hygiene supplies you will need after discharge.
- Report fever, active infection or a significant change in symptoms before the planned date.
- Confirm the hospital or day-care facility, arrival time and written estimate in advance.
Recovery
Recovery After Piles Treatment and Return to Work
Recovery differs enormously between an office procedure, laser treatment and excisional surgery, which is why a single "number of days" quoted online is rarely useful. What follows is a general guide. Your own timeline is confirmed by the treating team based on your procedure, your work and your progress.
The first 48 hours
Follow the discharge plan for pain relief, diet, fluids, hygiene and activity. Some discomfort or a small amount of bleeding is expected after some procedures; the amount that is normal for your procedure must be explained to you before you go home.
The first bowel movement
This is what most patients worry about, and it is worth preparing for. Soft stool, stool-softening medicine, gentle cleaning and not straining are the priorities. Anxiety leading to deliberately delayed bowel movements makes the first one harder, not easier.
Returning to work and normal activity
Timing depends on the procedure, symptom control, the physical demands of your job, whether you drive, and your general health. Office-based procedures often allow a return within a few days. Excisional surgery usually needs longer. Get personalised clearance rather than relying on a generic figure.
Follow-up review
Review assesses symptom relief, healing, bowel habit and any unexpected problems. Persistent or recurrent bleeding needs reassessment even where piles have previously been treated.
Contact the treating team promptly for:
- Bleeding greater than the amount described in your discharge instructions
- Increasing pain not controlled by the medicines you were given
- Fever, pus-like discharge or worsening swelling
- Difficulty passing urine
- Persistent vomiting or inability to drink
- Severe constipation despite the agreed plan
Heavy bleeding, fainting, severe weakness or rapidly worsening symptoms require urgent assessment, not a routine message.
Balanced Consent
Risks, Limitations and Recurrence
Risk depends on the procedure and on your health. The discussion before treatment should cover common temporary effects, important uncommon complications, the alternatives, and what is likely to happen without any intervention.
- Pain or discomfort
- Early or delayed bleeding
- Infection or abscess
- Swelling or thrombosis
- Difficulty passing urine
- Constipation or painful bowel movements
- Reaction to medicines or anaesthesia
- Delayed wound healing
- Anal narrowing after some operations
- Urgency, leakage or continence change in uncommon cases
- Persistent symptoms or recurrence
- Need for a further procedure
This list is not exhaustive. Procedure-specific consent information is provided before treatment.
Will piles come back?
They can. No treatment removes every possibility of future symptoms. Recurrence depends on the original grade, the procedure performed, tissue support, bowel habit and follow-up. Recurrent bleeding should be reassessed rather than assumed to be the same problem returning.
- Aim for soft, formed stool rather than swinging between constipation and diarrhoea
- Increase fibre gradually where medically appropriate
- Take fluids appropriate to your own health conditions
- Avoid long toilet sittings and repeated straining
- Stay physically active within medical advice
- Review medicines or conditions that affect bowel habit
- Attend follow-up if symptoms persist or return
What about continence? Will I lose control?
This is a common and reasonable fear, particularly among patients who have read about sphincter injury. Modern haemorrhoid procedures are planned to preserve the sphincter, and significant continence change is uncommon. It is not impossible, which is why it appears on the consent list above, and why the choice of procedure is influenced by any pre-existing weakness, previous anorectal surgery or obstetric injury. Tell the clinician if you already have any urgency or leakage before treatment.
Assessment-Based Estimate
What Affects the Cost of Piles Treatment in Agra?
The final cost depends on the diagnosis, grade, procedure, anaesthesia, facility, investigations, medicines, consumables and follow-up. A single advertised price is usually misleading, because a consultation, an office procedure, laser treatment and excisional surgery consume very different resources. A written, itemised estimate is provided once the treatment plan is agreed.
| Factor | Why it changes the estimate |
|---|---|
| Diagnosis and grade | Internal, external, mixed and thrombosed disease follow different pathways. |
| Selected treatment | Conservative care, an office procedure, laser treatment and surgery differ substantially in resource use. |
| Anaesthesia | Local, sedation, regional and general anaesthesia have different requirements. |
| Facility and length of stay | Theatre, room, nursing and observation charges vary by setting. |
| Investigations | Blood tests, endoscopy or further bowel evaluation may be required. |
| Medicines and consumables | Requirements depend on the procedure and other medical conditions. |
| Follow-up | Review, dressings, bowel-care management or further treatment may add to the total. |
Insurance, cashless treatment and government schemes
Some haemorrhoid procedures may be covered by health insurance policies or government schemes, though many policies apply a waiting period for piles specifically, and day-care cover varies by policy. Bring your policy details and card to the consultation so that eligibility, pre-authorisation and any waiting period can be checked before a date is fixed. Ask the clinic directly which insurers and schemes are currently accepted at the facility where your procedure would be performed.
Relevant Specialist Experience
Piles Assessment with Dr. Himanshu Yadav
Dr. Himanshu Yadav is an M.Ch.-qualified Surgical Gastroenterologist practising in Agra. His relevant expertise includes proctology, colorectal surgery, and laser surgery for haemorrhoids and related anorectal conditions.
Dr. Yadav’s approach is to confirm the diagnosis first, distinguish piles from other causes of bleeding or pain, begin with non-surgical care where appropriate, and discuss laser or surgical treatment only when the expected benefit justifies the risks and recovery.
| Qualifications | M.S.; M.Ch. in Surgical Gastroenterology from SGPGIMS, Lucknow |
|---|---|
| Colorectal and proctology credentials | FISCP; FALS in Colorectal Surgery; MMAS in Colorectal Surgery |
| Minimal-access surgery | FMAS |
| Professional roles | Past Chairman, Central Zone AMASI; approximately a decade on the AMASI Executive Committee; National Coordinator, Safe Laparoscopic Cholecystectomy Programme, AMASI |
| Relevant expertise | Proctology, colorectal surgery, and laser surgery for haemorrhoids and related anorectal conditions |
| Registration | Medical Registration No. 52309 |
| Languages | Hindi and English |
Dr. Himanshu Yadav has more than 20 years of surgical experience and has performed more than 22,000 procedures across his overall surgical practice, as at .

Consultation in Agra
Visit Dr. Himanshu’s Clinic, Delhi Gate Road
Contact the clinic to request a suitable consultation time and to confirm which reports to bring. A requested date or time is confirmed by the clinic before it is booked.
| Clinic | Dr. Himanshu’s Clinic |
|---|---|
| Address | First Floor, Shanti Madhuvan Plaza, near Pushpanjali Hospital, Delhi Gate Road, Agra, Uttar Pradesh 282002 |
| OPD with Dr. Yadav | 12 PM–6 PM |
| Operative hours | 8 AM–12 PM |
| Primary phone | +91 9897794208 |
| Alternate phone | +91 8630729225 |
| +91 8171944038 (opens in a new tab) | |
| drhimanshuyadav@gmail.com | |
| Access | Parking, wheelchair access and lift access available |
Finding the clinic
The clinic is on the first floor of Shanti Madhuvan Plaza on Delhi Gate Road, next to Pushpanjali Hospital, which is the landmark most auto and cab drivers in Agra recognise. There is lift access from the ground floor.
Travelling from outside Agra
The clinic is located in Agra; the places below are surrounding service areas and do not represent separate clinic branches. Patients attend from across the Agra region, including Mathura, Firozabad, Tundla, Shikohabad, Etah, Kasganj, Mainpuri, Hathras, Etawah, Fatehabad, Etmadpur, Kheragarh, Achhnera, Shamsabad and Dholpur. If you are travelling a long distance, telephone or message the clinic beforehand so that the consultation, any proctoscopy and the necessary blood tests can be planned for a single visit wherever possible. Bring all previous reports with you.
What to bring
- Current medicines and any allergies
- Relevant blood-test, endoscopy or pathology reports
- Previous treatment or operation records
- Health insurance card or policy details, if applicable
- A short written timeline of your symptoms, and your questions
Request Appointment Call Clinic WhatsApp (opens in a new tab) Get Directions (opens in a new tab) Full Clinic Details
Common Patient Questions
Frequently Asked Questions About Piles Treatment
These answers give general information about piles, diagnosis and treatment. They cannot establish the cause of an individual symptom or confirm whether a specific procedure is suitable for you.
Can piles be cured without surgery?
Often, yes. Most Grade I and many Grade II internal haemorrhoids improve with bowel-habit correction, adequate fibre, appropriate fluid intake and short-term symptom relief, without any procedure. Surgery becomes a serious consideration when bleeding is recurrent, prolapse is established, an external component is troublesome, or conservative measures have genuinely been tried and have not worked.
Is laser piles treatment suitable for every patient?
No. Laser haemorrhoidoplasty suits selected patients, most often those with bleeding Grade II or Grade III internal haemorrhoids. It is a poor choice where the main problem is a large external component or skin tags, in Grade IV prolapse, or where the cause of bleeding has not been established. Suitability is decided after examination, not from a description of symptoms over the phone.
Is piles surgery painful?
The procedure itself is performed under anaesthesia, so it is not painful at the time. Afterwards, discomfort varies considerably by method: office procedures such as band ligation usually cause the least, laser haemorrhoidoplasty generally causes less early pain than excisional surgery, and excisional haemorrhoidectomy typically causes the most, particularly with the first few bowel movements. Pain relief and stool softeners are planned in advance. No procedure can honestly be described as painless.
What are the four grades of piles?
The grades describe how far internal haemorrhoids prolapse. Grade I stays inside the anal canal. Grade II prolapses on straining and goes back by itself. Grade III prolapses and has to be pushed back manually. Grade IV stays prolapsed and cannot be easily reduced. The grading applies only to internal haemorrhoids; external haemorrhoids are not graded this way.
Is rectal bleeding always caused by piles?
No, and this assumption is the main reason serious bowel conditions are diagnosed late. Anal fissure, fistula, inflammatory bowel disease, polyps and colorectal cancer can all cause rectal bleeding. Piles are common, so they are often present at the same time as another cause. Any new, persistent or recurrent rectal bleeding should be examined, particularly over the age of 40, or where there is weight loss, a change in bowel habit, anaemia or a family history of bowel cancer.
How long does recovery take after piles treatment?
It depends entirely on the procedure. After an office procedure such as band ligation, many people resume normal activity within a few days. After laser haemorrhoidoplasty, early recovery is generally quicker than after conventional surgery, but bowel movements can still be uncomfortable for a period. After excisional haemorrhoidectomy, recovery is longer and healing continues for several weeks. Your own timeline also depends on your work, your general health and how your recovery progresses, so ask for a personalised estimate rather than relying on an advertised figure.
Can piles come back after laser treatment or surgery?
Yes. No haemorrhoid treatment eliminates the possibility of recurrence. The risk relates to the original grade, the procedure performed, the strength of the supporting tissue, and above all continuing bowel habits. Persistent constipation and straining after treatment are the commonest reason symptoms return. Any claim of zero recurrence should be treated with caution.
Will piles treatment affect my control over bowel movements?
Significant continence change is uncommon. Modern haemorrhoid procedures are planned to preserve the anal sphincter, and this is one reason the choice of procedure matters. The risk is higher where there is pre-existing sphincter weakness, previous anorectal surgery or obstetric injury, so tell the clinician if you already experience any urgency or leakage. It remains on the consent list because it is not impossible, and you should expect it to be discussed openly rather than dismissed.
What is the difference between piles, an anal fissure and an anal fistula?
Piles are enlarged, symptomatic vascular cushions that typically cause bleeding, prolapse or a lump. An anal fissure is a tear in the anal lining that typically causes sharp pain during and after passing stool, often with a small amount of bright-red blood. An anal fistula is an abnormal tract between the anal canal and the skin, typically causing recurrent swelling, abscesses and persistent pus discharge. All three can coexist, and each has a different treatment pathway, which is why examination matters more than matching your symptoms to a description online.
Do I need to stop my blood thinners before piles treatment?
Do not stop any blood thinner on your own. Whether warfarin, a newer oral anticoagulant, aspirin or clopidogrel is adjusted, and when, is decided together with the doctor who prescribed it, because stopping carries its own risks. Bring the full list to your consultation. Blood thinners also influence which procedure is preferable — band ligation, for example, is generally avoided in patients who are anticoagulated.
I have diabetes. Does that change piles treatment?
It changes the planning rather than ruling treatment out. Glucose control is reviewed before a planned procedure because it affects wound healing and infection risk. Separately, any perianal pain, swelling or discharge in a person with diabetes should be assessed promptly rather than managed at home, because perianal infection can progress quickly when diabetes is poorly controlled.
Can piles be treated during pregnancy?
Piles are common in pregnancy and frequently improve after delivery. Treatment during pregnancy is usually conservative and focuses on preventing constipation, and the choice of medicines is restricted. Elective procedures are generally deferred until after childbirth. Any bleeding during pregnancy should be reported to your treating doctor rather than assumed to be piles.
When is bleeding from piles an emergency?
Seek urgent assessment if bleeding is heavy or will not stop, if you feel dizzy, faint, breathless or unusually weak, if stools are black or tar-like, or if severe pain and swelling are worsening rapidly with fever. These features suggest either significant blood loss or a cause other than simple piles, and they warrant an emergency department rather than a routine clinic appointment.
Will I need to be admitted to hospital?
Many office procedures need no admission at all. Laser and operative treatment are often planned as day care, but observation may be advised depending on the procedure, the anaesthesia used, pain control, bleeding, whether you can pass urine, your other health conditions and the support available at home. A same-day discharge cannot honestly be promised before assessment.
What affects the cost of piles treatment in Agra?
The main drivers are the diagnosis and grade, the procedure selected, the type of anaesthesia, the facility and length of stay, any investigations required, medicines and consumables, and follow-up. This is why a single advertised price is usually misleading. Ask for a written, itemised estimate once the treatment plan is agreed, and check your insurance policy for any waiting period that applies specifically to piles.
Which doctor treats piles — a general surgeon, a gastroenterologist or a proctologist?
Haemorrhoids are managed by surgeons who treat anorectal disease. In India these are usually general surgeons, colorectal surgeons, surgical gastroenterologists or surgeons practising as proctologists. What matters more than the label is whether the surgeon assesses the whole anorectum, can distinguish piles from fissure, fistula and other causes of bleeding, offers more than one treatment method, and arranges further bowel evaluation when it is indicated. "Proctologist" is not a separate recognised postgraduate qualification in India, so ask what the underlying surgical qualification is.
Bawaseer ka ilaaj bina operation ke ho sakta hai?
Haan, kai maamlon mein. Grade I aur bahut se Grade II ke andaruni bawaseer fibre, sahi maatra mein paani, kabz ka ilaaj aur bowel habit theek karne se hi behtar ho jaate hain — operation ki zaroorat nahin padti. Operation tab zaroori ho sakta hai jab khoon baar-baar aaye, massa bahar aa jaaye aur wapas na jaaye, bahri massa pareshaan kare, ya dawa aur parhez se aaram na mile. Sahi salah janch ke baad hi di ja sakti hai.
Kya laser se bawaseer ka ilaaj bilkul dard rahit hai?
Nahin. Laser se ilaaj mein aam taur par shuru ke dinon mein dard kam hota hai, lekin "bilkul dard nahin hoga" kehna sahi nahin hai. Procedure anaesthesia mein hota hai, isliye us waqt dard nahin hota. Baad mein, khaas taur par pehle kuch bowel movements ke samay, takleef ho sakti hai. Iske liye dard ki dawa aur stool softener pehle se hi di jaati hai. Laser har mareez ke liye theek nahin hai — bahri massa ya Grade IV mein iska nateeja kam rehta hai.
References and Further Reading
The general clinical statements on this page are consistent with current guidance from recognised colorectal surgical bodies and national health information services. This page is not a substitute for individual medical advice.
- Hawkins AT, et al. The American Society of Colon and Rectal Surgeons Clinical Practice Guidelines for the Management of Hemorrhoids. Diseases of the Colon & Rectum. 2024;67(5):614–623. ASCRS guideline (opens in a new tab)
- National Institute of Diabetes and Digestive and Kidney Diseases. Treatment of Hemorrhoids. NIDDK patient guidance (opens in a new tab)
- NHS. Piles (haemorrhoids). [Accessed 2 September 2026]. NHS patient guidance (opens in a new tab)
- Gonçalo Torrinha, et al. The effects of laser procedure in symptomatic patients with haemorrhoids: A systematic review. Frontiers in Surgery. 2022;9:1050515. Frontiers article (opens in a new tab)
- Wee IJY, Koo CH, Seow-En I, Ng YYR, Lin W, Tan EJK. Laser hemorrhoidoplasty versus conventional hemorrhoidectomy for grade II/III hemorrhoids: a systematic review and meta-analysis. Annals of Coloproctology. 2023;39(1):3–10. Article (opens in a new tab)
Sources accessed 2 September 2026. If you believe any information is inaccurate or out of date, contact the clinic.
Piles Consultation in Agra
Discuss Rectal Bleeding, Prolapse or Piles Symptoms
A consultation can confirm whether your symptoms are caused by piles, establish the grade and external component, and set out the conservative, laser and surgical options that actually apply to you. Request a time and wait for the clinic to confirm it before treating the slot as booked.
Request an Appointment Call +91 9897794208 WhatsApp (opens in a new tab) Get Directions (opens in a new tab)